



Text version
Relapse Risk After Stopping Antipsychotics in Pregnancy
When discussing medication with a patient who is pregnant or contemplating pregnancy, a risk-versus-risk conversation is an essential component of the visit. This discussion weighs the risks of fetal exposure to a medication against the risks to maternal mental health if the medication is discontinued or never started.
Yet surprisingly little has been published that characterizes the recurrence risk of psychotic and bipolar disorders after antipsychotics are discontinued in pregnancy. So how are we supposed to give meaningful guidance? A recent cohort study published in JAMA Network Open analyzed decades’ worth of national birth register data from Denmark and Sweden to offer insight, and finally some concrete numbers, for this clinical conversation.
Download PDF and other files
Danish and Swedish Register Cohort
The authors of this study set out to assess the risks of antipsychotic discontinuation using data from thousands of women in Denmark and Sweden who were diagnosed with bipolar disorder or a primary psychotic disorder.
The women had discontinued their antipsychotic treatment either preconception or during pregnancy, and they were matched in equal number to a control group of women who continued their antipsychotic. For each group, the outcome assessed was severe psychiatric relapse, defined as inpatient treatment for a psychiatric disorder during pregnancy and up to three months postpartum.
Over 80% Discontinued Their Antipsychotic
Their first major finding was that rates of antipsychotic discontinuation were extremely high: over 80% of the cohort. This was true in both countries and for both primary psychotic and bipolar disorders. In fact, discontinuation was so prevalent that it affected the study’s statistical power and the authors’ ability to run some of their intended analyses.
So we see loud and clear here that concerns about fetal exposure have historically prevailed in those risk-versus-risk discussions. Continuation rates were notably higher in women who gave birth between 2016 and 2022. That makes sense to me, because by then a lot more reassuring evidence had been published indicating that antipsychotic exposure in utero was not expected to increase the risk of congenital malformations.
Download PDF and other files
Stopping Raised Relapse Risk in Psychosis
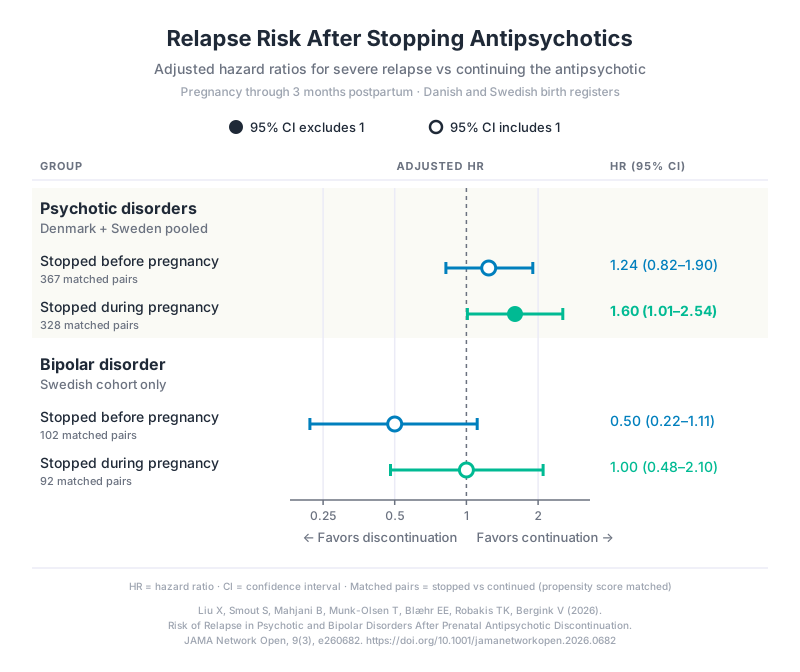
The bottom-line takeaway of their analysis was that for women with primary psychotic disorders, discontinuing antipsychotics during pregnancy was associated with a 60% increased risk of severe psychiatric relapse during pregnancy or the first three months postpartum. Discontinuing antipsychotics preconception was associated with a 24% increased risk of severe psychiatric relapse.
For women with bipolar disorder, discontinuation was not associated with changes in relapse risk, either preconception or during pregnancy. However, power was limited by the small sample size.
Counsel Early and Explore Motivations
So what should we do with this information, and how will it change how we counsel patients? Here’s how I would think about these findings practically.
First of all, it’s important to remember that half of all pregnancies are unplanned. The high rate of discontinuation in the study highlights the importance of the timing of counseling. Early in treatment, we should be asking patients what they would want to do if they became pregnant, in order to avoid abrupt self-discontinuation down the road.
But the vast majority of women in the study discontinued even preconception. Antipsychotics and hyperprolactinemia can make it more difficult to conceive, so it’s possible that this phenomenon is due in part to fertility concerns rather than teratogenicity concerns. We’ll want to pay attention to that, because understanding a patient’s motivations for discontinuation is key to addressing their concerns and developing a relevant treatment plan.
Download PDF and other files
Clinical Scenarios
Let’s imagine now that we’re walking through a few different clinical scenarios based on the data from this study. Which pregnant patients with psychotic or bipolar disorders should be advised to continue antipsychotics throughout pregnancy? And which might reasonably attempt discontinuation before conception?
Pregnant Patient With a Psychotic Disorder
For the patient who is already pregnant, I think the study makes a strong case against discontinuing antipsychotics during pregnancy for women with primary psychotic disorders. While the study could only assess that inpatient admissions increase if the medication is discontinued, we can reasonably assume that the rate of less severe mental health decompensations probably increases as well. These recurrences can be highly impairing and distressing, even if they never reach criteria for psychiatric hospitalization.
Another key point is that not only is discontinuation during pregnancy associated with a higher risk of severe relapse, but fetal exposure has already occurred. So discontinuing the antipsychotic during pregnancy confers a very clear risk to maternal mental health with a much less clear fetal benefit.
I also try to help women understand what the data do show about the risks of fetal exposure, so that they can make a more informed decision about their treatment regimen. I highlight that:
- Second-generation antipsychotics have not consistently demonstrated an increased risk of congenital malformations, although some agents have been associated with an increased risk of gestational diabetes
- All antipsychotics are associated with an increased risk of abnormal involuntary muscle movements in the newborn after delivery, which are most often self-limited if they do occur
The patient and I will also reflect together on her past experiences of being quite ill. We compare the potential risks of medication exposure with the potential risks to the fetus from the types of behaviors she has historically engaged in when symptomatic.
Preconception Patient With a Psychotic Disorder
If a woman with a primary psychotic disorder is preconception, I would counsel that her risk of severe relapse is still increased, and that the study can’t be interpreted to mean that those without a severe relapse were well and at their baseline. If her primary motivation for discontinuation is to improve her fertility, I talk with her about restarting the medication after she conceives.
Patient Determined to Discontinue
For any patient who ultimately feels strongly about discontinuing her antipsychotic for the duration of her pregnancy, I would recommend very close monitoring. I would also obtain a release of information to be able to communicate with those close to her in case psychosis re-emerges and impairs insight.
One thing I recommend is asking patients, when they’re well, what their initial presenting symptoms tend to be during a recurrence. Then, when I liaise with the rest of their care team, such as their obstetrician, I highlight those symptoms as key questions to ask about at each touchpoint.
I would also discuss with the patient ahead of time what her threshold would be to start the medication again if her mood began to change. And I would assess her openness to electroconvulsive therapy (ECT) as a nonpharmacologic treatment option during pregnancy. If she’s still well at delivery, we would discuss restarting the medication postpartum.
Patient With Bipolar Disorder
Where the data here are a little murkier is bipolar disorder. Prior studies demonstrated a very clearly elevated risk of maternal mental health decompensation when lithium was discontinued due to pregnancy. In contrast, this study didn’t find comparably compelling evidence that discontinuing an antipsychotic was associated with severe relapse.
However, I wouldn’t rush to discontinue your patient’s antipsychotic or write it off as ineffective, for two reasons:
- Most of the women with bipolar disorder who discontinued antipsychotics were taking another mood stabilizer, like lithium or lamotrigine. So the findings don’t necessarily reflect the risk of discontinuing antipsychotic monotherapy.
- Most bipolar disorder recurrences in pregnancy are depressive episodes, which are less likely to result in hospital admission. This particular study couldn’t capture all the relevant clinical outcomes we would want to know about, which can confer high morbidity and more negative maternal and neonatal outcomes.
That said, my takeaway would be this: if your patient is preconception, euthymic, and taking a mood stabilizer like lamotrigine or lithium in addition to the antipsychotic, this study offers support that it may be reasonable to trial discontinuing the antipsychotic before conception in order to minimize polypharmacy.
Individualized Decisions, More Data Needed
I’ll conclude by saying that, at the end of the day, these conversations will always be individualized to each patient’s needs, priorities, and clinical history. It’s great to see more data coming out that can help patients make informed decisions about their mental health management. Hopefully we’ll see more studies in the future that bring additional clarity about clinical considerations for antipsychotic use during pregnancy.
Download PDF and other files
Abstract
Risk of Relapse in Psychotic and Bipolar Disorders After Prenatal Antipsychotic Discontinuation
Xiaoqin Liu; Shelby Smout; Behrang Mahjani, et al
Importance
Antipsychotics are increasingly used in the perinatal period. However, evidence of their effectiveness in the perinatal population is limited.
Objectives
To examine the risk of severe psychiatric relapse during the perinatal period associated with discontinuation of antipsychotic treatment before or during pregnancy in women with primary psychotic disorders or bipolar disorder.
Design, Setting, and Participants
This cohort study used linked Danish and Swedish national birth registers to identify pregnancies leading to singleton live births from 1998 to 2022 in Denmark and from 2007 to 2017 in Sweden. Women diagnosed with psychotic disorders or bipolar disorder, with a gestational age between 154 and 315 days, and 2 or more antipsychotic prescriptions filled within 1 year before pregnancy were included. Data were analyzed from August 2024 to October 2025.
Exposure
The exposure of interest was antipsychotic discontinuation. Discontinuation was defined as no prescription refill within the expected prescription duration plus a 60-day grace period. Women were classified into groups: prepregnancy discontinuation, pregnancy discontinuation, and continuation. The prepregnancy discontinuation group was matched 1:1 to the continuation group, and the pregnancy discontinuation group was separately matched 1:1 to the same continuation group.
Main Outcomes and Measures
The outcome of interest was severe psychiatric relapse in the perinatal period. Hazard ratios (HRs) were estimated for psychiatric relapse, defined as inpatient treatment for psychiatric disorders during pregnancy and up to 3 months post partum, using a stratified Cox proportional hazards regression model.
Results
A total of 2000 women with primary psychotic disorders (1265 from Denmark and 735 from Sweden) and 1292 women with bipolar disorder (341 from Denmark and 951 from Sweden) were included. The mean (SD) age was 30.8 (6.0) years for women with psychotic disorders and 29.1 (7.7) years for women with bipolar disorder. For women with psychotic disorders discontinuing antipsychotics before pregnancy, the adjusted HR (AHR) of psychiatric relapse was 1.24 (95% CI, 0.82-1.90) compared with continuation. Pregnancy discontinuation had a higher point estimate for relapse risk (328 pairs; AHR, 1.60 [95% CI, 1.01-2.54]) compared with continuation of antipsychotics. Among women with bipolar disorder, prepregnancy discontinuation (102 pairs; AHR, 0.50 [95% CI, 0.22-1.11]) and pregnancy discontinuation (92 pairs; AHR, 1.00 [95% CI, 0.48-2.10]) point estimates did not show an increased risk of severe relapse, but statistical power was limited.
Conclusions and Relevance
In this cohort study, women with psychotic disorders who discontinued antipsychotic treatment during pregnancy were at a higher risk of severe relapse and the results for those who discontinued prepregnancy suggest a possible increase in risk, compared with those who continued, which aligns with findings observed beyond the perinatal period; results in women with bipolar disorder were inconclusive. There is an urgent need to investigate the effectiveness of antipsychotics on both severe and nonsevere relapses in the perinatal period in prospective clinical cohort studies.
Reference
Liu, X.; Smout, S.; Mahjani, B.; Munk-Olsen, T.; Blæhr, E.; Robakis, T. et al. (2026). Risk of Relapse in Psychotic and Bipolar Disorders After Prenatal Antipsychotic Discontinuation. JAMA Netw Open; 9(3):e260682.
